The EVOKE Trial Aftermath: Why GLP-1 Drugs Didn't Save Alzheimer's — Yet
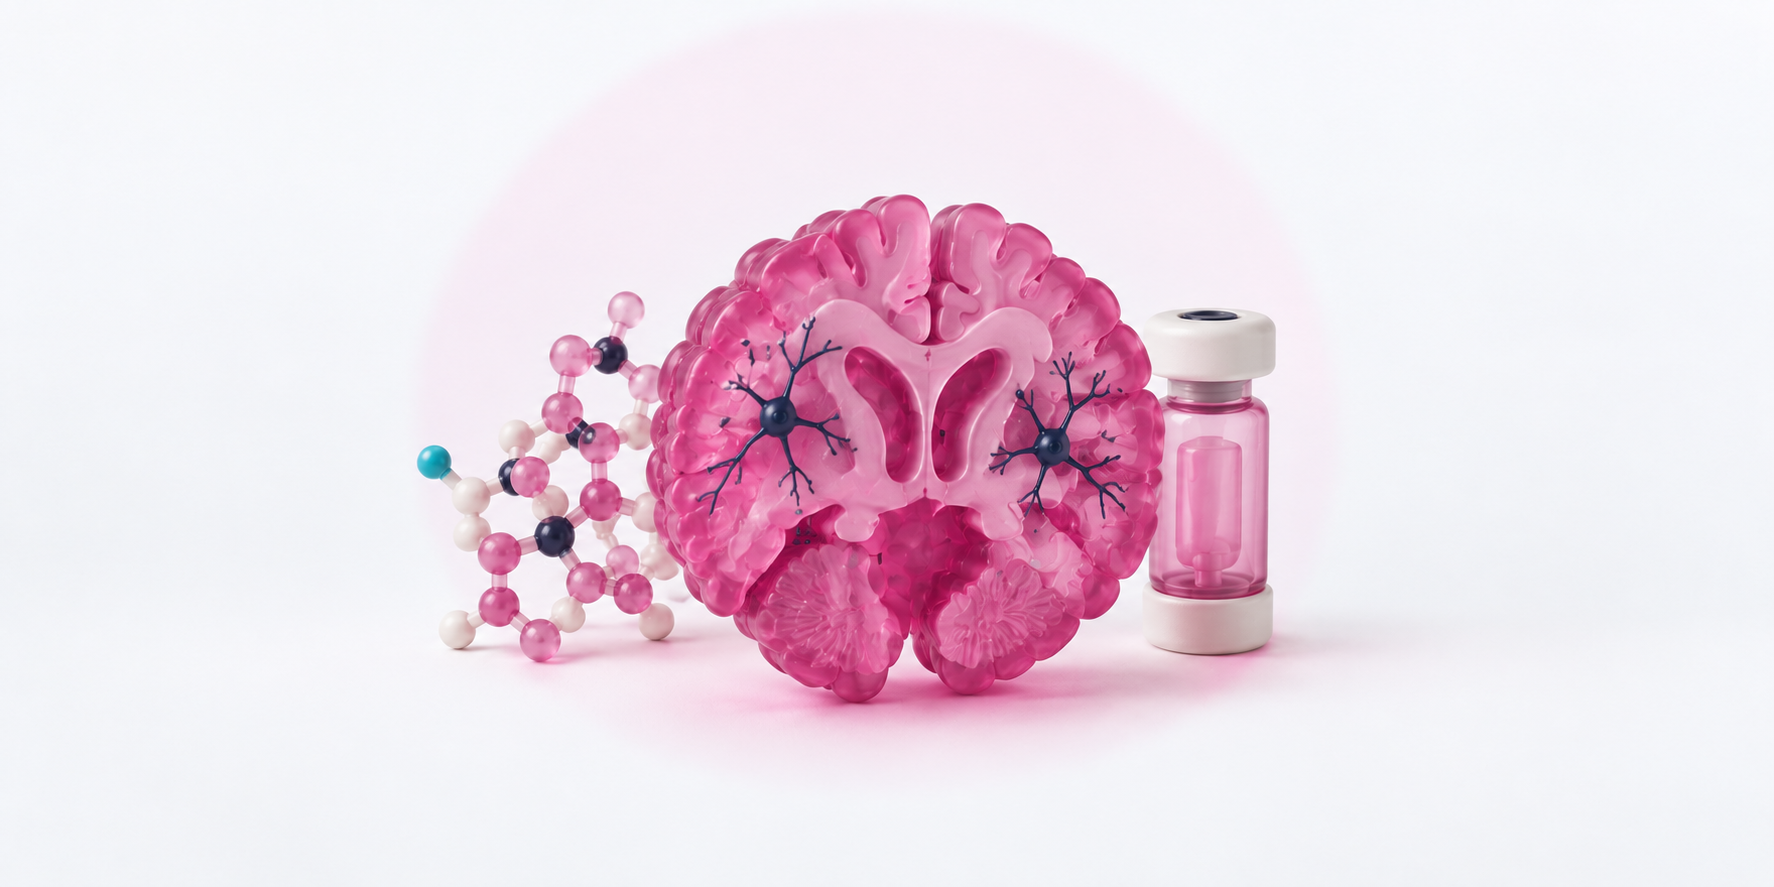
Semaglutide's Phase 3 EVOKE trial in early Alzheimer's missed its primary endpoint — but inflammatory markers fell, and brain-penetrant successors are already lining up.
- #GLP-1
- #Alzheimer's
- #EVOKE
- #semaglutide
- #neurodegeneration
- #clinical trials
- #pharmacology
For three years, neurologists watched semaglutide with cautious optimism. Animal studies suggested GLP-1 receptor agonists could quiet the brain inflammation that accompanies Alzheimer''s disease. Real-world data from diabetics taking the drug hinted at lower dementia incidence. The Phase 3 EVOKE program was set up to settle the question. In 2026 it read out — and the headline answer was no.
That single sentence undersells what actually happened. EVOKE missed its primary cognitive endpoint, but the trial generated a useful map of where the GLP-1 hypothesis is right, where it is wrong, and what the next generation of drugs has to do better.
What EVOKE actually tested
EVOKE and EVOKE+ together enrolled roughly 4,000 participants with early-stage Alzheimer''s disease, defined by amyloid-positive imaging and mild cognitive impairment or mild dementia. Participants received daily oral semaglutide or placebo for approximately two years. The primary endpoint was the Clinical Dementia Rating Sum of Boxes (CDR-SB) — a standard composite that captures memory, judgment, community affairs, home and personal care.
At week 104 the difference between semaglutide and placebo did not reach statistical significance. The pre-specified hypothesis — that GLP-1 signaling would slow clinical decline — was not supported by the data.
Why brain penetrance is the most plausible explanation
Semaglutide is a relatively large peptide that does not cross the blood-brain barrier well. The behavioral effects we see — appetite suppression, satiety — are mediated by the small handful of brain regions where peripheral GLP-1 signals can reach, primarily through circumventricular organs like the area postrema.
For Alzheimer''s, that is the wrong target geography. The pathology lives deep in the hippocampus, entorhinal cortex, and association areas. If GLP-1 receptor agonists are going to slow neurodegeneration, drug levels in those tissues need to be meaningful — and EVOKE may simply have shown that oral semaglutide does not get there in adequate concentrations.
The positive signal: inflammation fell
Pre-EVOKE work, including a widely-cited post-hoc analysis of the EXSCEL cardiovascular outcomes trial, had shown that GLP-1 receptor agonists lower circulating inflammatory markers associated with Alzheimer''s risk. EVOKE''s biomarker substudies pointed in the same direction. Even without a clinical benefit on CDR-SB, the underlying biology was doing something.
This is meaningful because it tells you the target is real — chronic low-grade neuroinflammation does respond to GLP-1 signaling. The trial did not show that hitting that target produces a measurable cognitive benefit at two years with a non-brain-penetrant drug. Those are very different conclusions, and the field is increasingly careful to separate them.
Three classes of drug that may yet succeed
1. Brain-penetrant small molecules
Several companies are now in late preclinical or early clinical development with orally bioavailable small molecules that activate GLP-1 receptors and actually cross the blood-brain barrier. If brain penetrance is the limiting factor in EVOKE, these compounds should produce different biomarker dynamics in the CNS within months of dosing.
2. Dual and triple incretin agonists
Tirzepatide combines GLP-1 and GIP receptor activity. Retatrutide adds glucagon receptor agonism on top — a triple agonist. Both produce more aggressive weight loss and metabolic effects than semaglutide. Whether that translates to meaningful CNS effects depends on the same penetrance question, but the broader hormonal signal may engage pathways semaglutide misses.
3. Combination with anti-amyloid antibodies
Lecanemab and donanemab are the first disease-modifying Alzheimer''s therapies to win approval. Their effect on cognition is modest. Combining amyloid clearance with anti-inflammatory GLP-1 signaling is the obvious next experiment — and several trial designs are already public.
What this means for students entering the field
EVOKE is a clean example of a phenomenon you''ll see repeatedly in clinical research: a hypothesis can be biologically correct in principle but wrong about the molecule chosen to test it. The press will read a negative trial as the end of the story. The science usually reads it as a refinement of the question.
If GLP-1 signaling in the brain matters for Alzheimer''s — and the inflammatory biomarker data suggests it does — then the next decade will be about engineering molecules that engage that signaling at the right concentrations in the right tissues. EVOKE didn''t close the door. It just showed where the door is.
Reactions
From QuizLab
Test Your Knowledge
Quizzes on the same ground as this article. Pick one and see how much stuck.
- PharmacologyIntermediatePharmacokinetics14questionsStart Quiz
- PharmacologyIntermediatePharmacodynamics13questionsStart Quiz
- PharmacologyAdvancedAutonomic Pharmacology13questionsStart Quiz
- PharmacologyBeginnerDrug Development10questionsStart Quiz
- PharmacologyAdvancedAntibiotic Mechanisms9questionsStart Quiz
- PharmacologyIntermediateNSAIDs & Opioid Analgesics11questionsStart Quiz
Keep Reading
More from Scribe
Articles on related ground, and the newest from Scribe.
 Industry News
Long COVID in 2026: What the RECOVER Trials Ruled In, What They Ruled Out
NIH spent $1.15 billion on the RECOVER program to test long-COVID treatments. The 2026 readouts retired some hypotheses and elevated others — baricitinib, low-dose naltrexone, and semaglutide.
biofideX4 min read Industry News
Pig Hearts and Kidneys in Humans: The 2026 Clinical Trial Era of Xenotransplantation
The FDA cleared the first US clinical trials in 2026 — United Therapeutics' 10-edit UKidney and eGenesis's 69-edit donor pigs. Here's what the science actually says.
biofideX5 min read Industry News
The Antibiotic Pipeline Is Almost Dry — Inside the 2026 Resistance Crisis
Only 6 of 27 antibiotics in active clinical development hit WHO priority pathogens with truly novel mechanisms. AMR is one of the few major health crises getting worse on schedule.
biofideX5 min read Industry News
The 5-Year Personalized mRNA Cancer Vaccine Data Just Read Out — Here's What It Means
Moderna and Merck's intismeran autogene cut melanoma recurrence-or-death by 49% at five years when combined with pembrolizumab. The platform is now expanding to lung, kidney, and bladder cancer.
biofideXMay 27, 20265 min read